 metaboliq
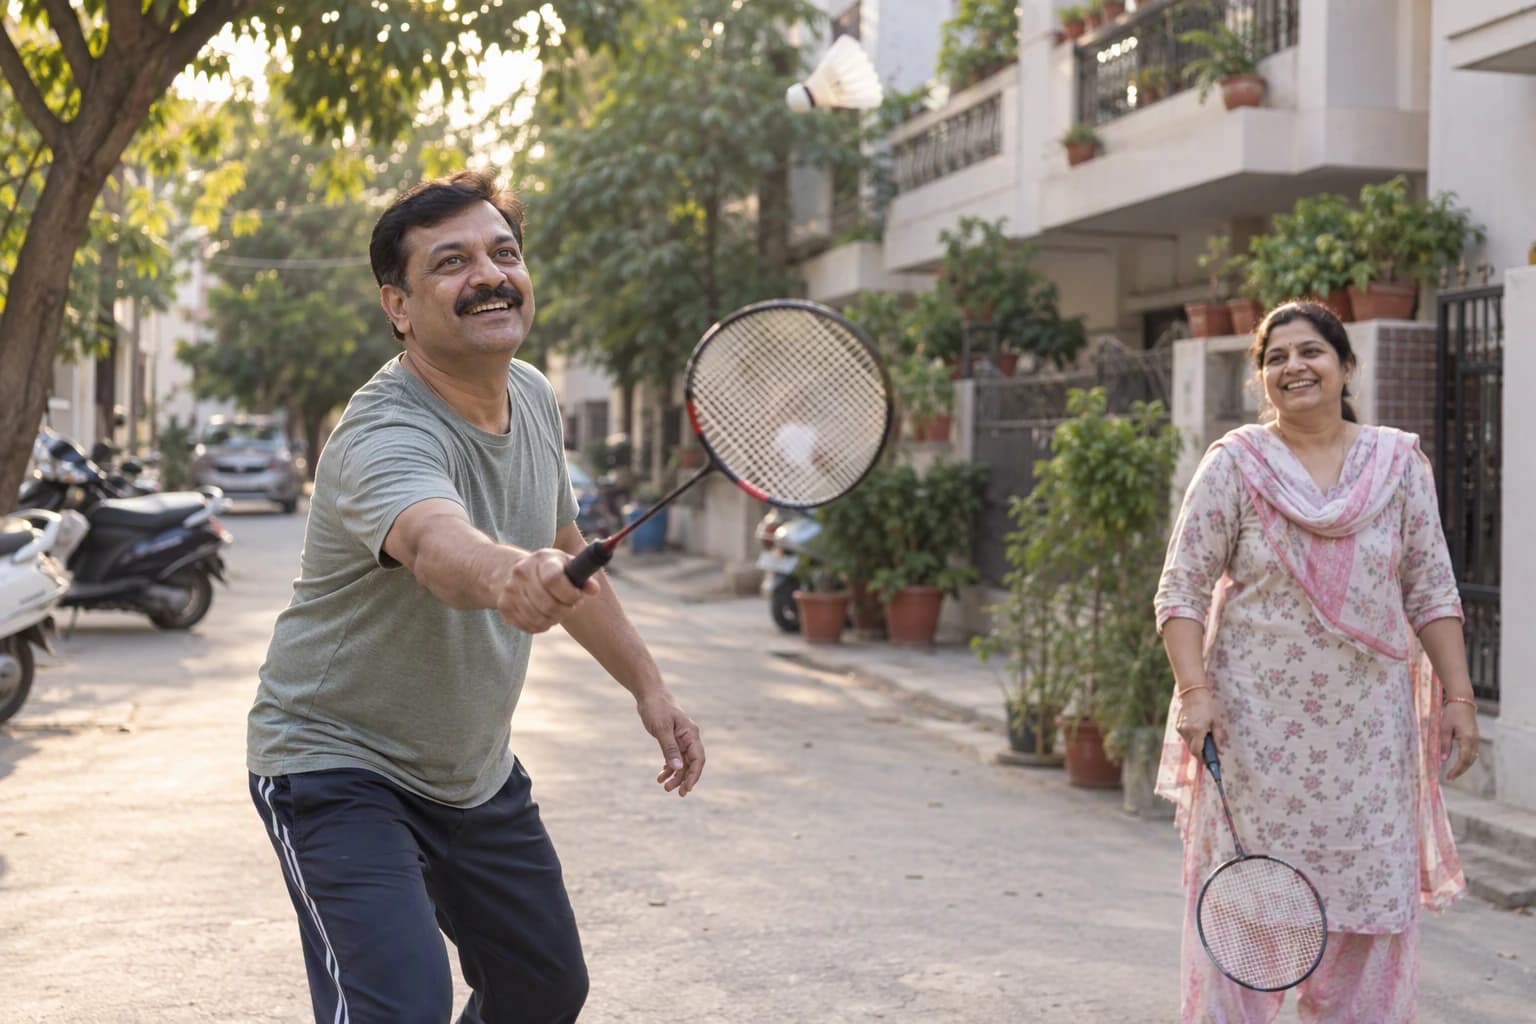
Ramesh is 46 and trades in cotton yarn in Kanpur. His annual check-up report came back with four numbers in bold: triglycerides, HDL cholesterol, fasting sugar and blood pressure. None was dramatically high, and his doctor wrote two words at the bottom of the page: metabolic syndrome. Ramesh had never heard of it. His wife has already searched it twice and found pages that frightened her. Ramesh is a composite of the readers who ask this, not a real patient.
Metabolic syndrome is a cluster of risk factors that tend to travel together: a large waist, high triglycerides, low HDL cholesterol, raised blood pressure and raised fasting sugar. Having three of the five makes the diagnosis. For Indians, the waist cut-off is lower than for Europeans. It raises the risk of diabetes and heart disease, and steady lifestyle change improves every part of it.
What is metabolic syndrome?
It is a name for five risk factors that often appear together and share a common driver, which is usually insulin resistance with fat stored around the belly and organs. The international definition agreed in 2009, which George Alberti's group set out, makes the diagnosis when any three of the five are present.
Ramesh's report fits it neatly. His waist, measured by the nurse at the lab, is 98 cm. His triglycerides are 212, his HDL is 36, his blood pressure was 138 over 88, and his fasting sugar 108. That is all five. None of them alone would worry a doctor much. Together they describe a body that is struggling to handle food and fat, years before diabetes or a heart problem shows up.
Sources: [1]
What are the five criteria, with Indian cut-offs?
The 2009 definition uses a waist of at least 90 cm for South Asian men and 80 cm for South Asian women. The other four are triglycerides of 150 mg/dL or more and HDL below 40 in men or below 50 in women. Then come blood pressure of 130 over 85 or higher, and fasting glucose of 100 or more. Being on treatment for any of these counts as meeting that criterion.
The Indian consensus statement led by Anoop Misra set the same lower waist thresholds for Asian Indians, because risk climbs at smaller waists here than in Europe. A man in Kanpur with a 92 cm waist is already over the line, while the same waist in London would not be. Ramesh can check his own number at home with a tape around his belly at the level of his navel, breathing out gently.
Why is metabolic syndrome so common in India?
South Asians carry more fat inside the abdomen and around the organs at the same body weight, and become insulin resistant at lower levels of overall fat. Anoop Misra and Naval Vikram's review describes how metabolic risk clusters at lower BMI and waist sizes in South Asians than in Europeans.
The national ICMR-INDIAB survey found abdominal obesity and abnormal lipids to be widespread across Indian states, alongside high rates of diabetes and prediabetes. Diet plays a part too. In V. Mohan's group's study of adults in Chennai, those who ate the most refined grain had higher odds of metabolic syndrome. Ramesh's day of white rice at lunch, three rotis at dinner and namkeen with evening tea is common, and it is part of his story.
What does the triglyceride and HDL pattern tell you?
Quite a lot about insulin resistance. Tracey McLaughlin's study at Stanford found that triglycerides, and the ratio of triglycerides to HDL, picked out insulin-resistant adults with useful accuracy. High triglycerides with low HDL is the signature lipid pattern of metabolic syndrome.
Ramesh's ratio is 212 divided by 36, almost six, which is high. That pattern responds well to the right changes. Cutting refined carbohydrate and sugar lowers triglycerides, often within weeks, and regular exercise nudges HDL up. Alcohol pushes triglycerides higher, so his two pegs on Saturday nights are worth reconsidering. A repeat lipid test three months after he starts is a good way to see whether the changes are working.
Sources: [5]
What does metabolic syndrome lead to?
Over the following years it raises the chance of type 2 diabetes, heart attack, stroke and fatty liver. Most people with it feel completely well, so it is found on reports rather than through symptoms. Anoop Misra's review notes that in South Asians these risks gather at lower waist sizes and lower body weights than in Europeans.
Ramesh feels fine, apart from getting a little breathless on the 22 steps up to his godown office. His father had a heart attack at 58 in the same city, in the same trade. That family history makes his report more urgent, and his doctor has asked for a repeat lipid test and an ECG. Ramesh's blood pressure, sugar and lipids are all still at the stage where food, walking and sleep can move them, which is the reason to act this winter.
Sources: [2]
Does metabolic syndrome affect the liver?
Very often. Fat stored inside the liver travels with belly fat and insulin resistance. Elisa Fabbrini and Samuel Klein's review describes how liver fat links closely to visceral fat and to poor insulin sensitivity, and how liver enzymes can stay normal even when the liver is fatty.
Ramesh's report showed his SGPT at the top of the normal range, which reassured him. An ultrasound of his abdomen, done for his acidity two years ago, had mentioned a grade 1 fatty liver that nobody followed up. It belongs to the same picture as his waist and his triglycerides. The changes that improve his metabolic syndrome usually take fat out of the liver too, and a repeat scan in a year would show it.
Sources: [8]
What should someone with metabolic syndrome eat?
Less refined carbohydrate and sugar, more protein and fibre, and fewer packaged snacks. Ranjit Mohan Anjana's analysis of Indian diets found that carbohydrate, mostly white rice and refined wheat, supplies most of the day's energy while protein is low. Shifting that balance is where most of the gain lies.
Ramesh's wife cooks for the whole family, so the changes have to suit everyone. Rice moves to one small katori at lunch, eaten after the dal and sabzi. Dinner becomes two phulkas with paneer or chana and a big salad, in place of three rotis with aloo. Evening namkeen gives way to roasted chana or a bowl of curd. Sugar in his tea halves, then halves again a month later.
Sources: [9]
Can metabolic syndrome go away?
Often, yes. In the Finnish Diabetes Prevention Study, Jaakko Tuomilehto's team gave adults with impaired glucose tolerance lifestyle counselling on weight, diet and activity. Their risk of developing type 2 diabetes fell by more than half compared with the control group.
A loss of even five to ten per cent of body weight improves every part of the syndrome. For Ramesh, at 92 kilos, that is five to nine kilos over the next six to twelve months. His plan has three parts. Rice drops to one small katori at lunch, with dal, sabzi and curd filling the plate. The Saturday pegs go down to one. He walks for 40 minutes each morning on the lane outside his house and plays badminton with his wife in the evenings.
Sources: [6]
Why does muscle matter for metabolic syndrome?
Muscle takes up most of the sugar from a meal. Ralph DeFronzo's work showed that insulin resistance in muscle is a central defect on the road to type 2 diabetes. More muscle, and muscle that is used, means less sugar left circulating and less turned into fat. Ramesh lifts yarn bales at his godown only on delivery days. Two short sessions a week at home, with squats, push-ups against the wall and a resistance band tied to the grille, make a difference alongside the walking.
We should say where we stand, since you are reading this on our site. Metaboliq is a doctor-led weight programme, and the aim we set with members is "Lose up to 20% of your body weight — and keep your muscle". Results vary; your doctor decides what is right for you. It starts with a home blood test that a doctor reads, because Ramesh's insulin and liver results would change how his plan is built.
Sources: [10]